
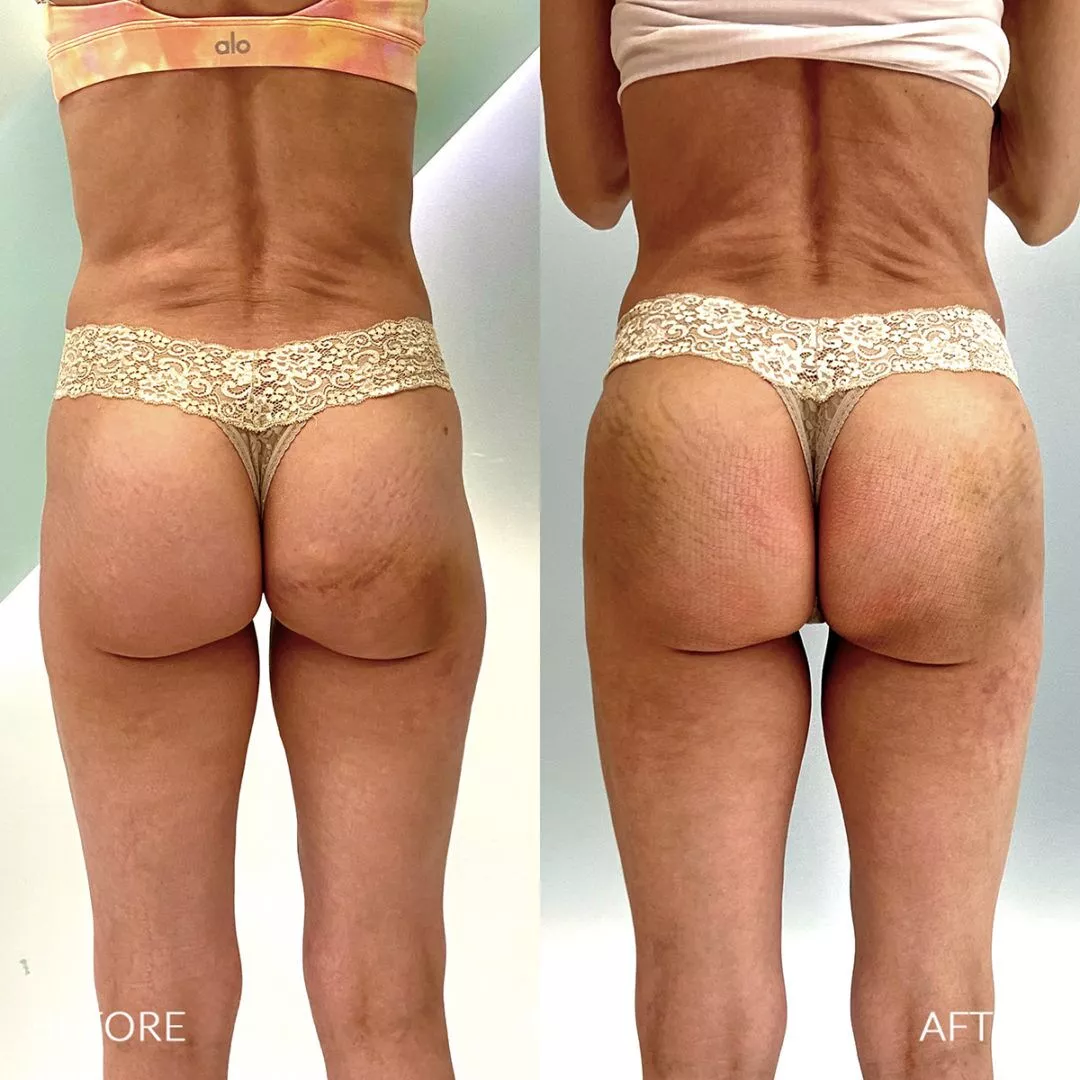


The hip dip is a structural gap, not a training problem
No amount of exercise changes bone structure. The inward dip at the outer hip is a gap created by your skeleton, and filling it means placing volume exactly where the curve breaks. That is what this patient came in for: one smooth line from waist to thigh, no interruption.
Dr. Emer uses your own fat, purified and blended with stem cells, PRP, exosomes and peptides, then transfers it into the hip dip and outer thigh to build that roundedness. The shift is visible during the session itself. The waist reads slimmer because the hip projects more. The outer thigh flows into the hip without a break.
What makes the fat survive
Not all fat transfer works the same way. Dr. Emer purifies the harvested fat first, removing fluid and damaged cells so only the healthiest tissue is placed. That purified fat is then blended with the patient's own stem cells, PRP, exosomes and peptides in a process he calls fusion. That step increases the chance the transferred fat will establish its own blood supply and survive long term.
After the procedure, hyperbaric oxygen therapy, IV support, massage, systemic peptides and increased circulation all support integration of the grafted fat. This is not weeks of bed rest. After the first few days, movement and light activity are encouraged. Compression garments are worn for one to two weeks.
The technique: curved cannula, small entry, precise placement
Dr. Emer reaches the hip dip through a small entry point using a curved cannula. That geometry makes placement more demanding, but it keeps incisions minimal. He works from the front first to shape the outer hip and thigh, then finishes the back to complete the curve. Each side receives multiple passes, building volume in half syringe increments until the contour matches the plan.
The discoloration visible during the session is normal. It is blood supply returning as the epinephrine wears off. By the next day, bruising is minimal. The shape continues to settle over the following weeks as the fat integrates.
Who this fits
This procedure is for women who want a rounder hip and a more defined waist to hip ratio using their own tissue, not implants or synthetic filler. Candidacy depends on having enough donor fat to harvest, realistic goals for the amount of projection that can be added, and a commitment to the aftercare plan that helps the fat survive.
What does your anatomy actually allow for? A consultation covers your structure, your goals, and whether fat transfer to the hips and outer thighs fits your plan. Book a consultation to find out.